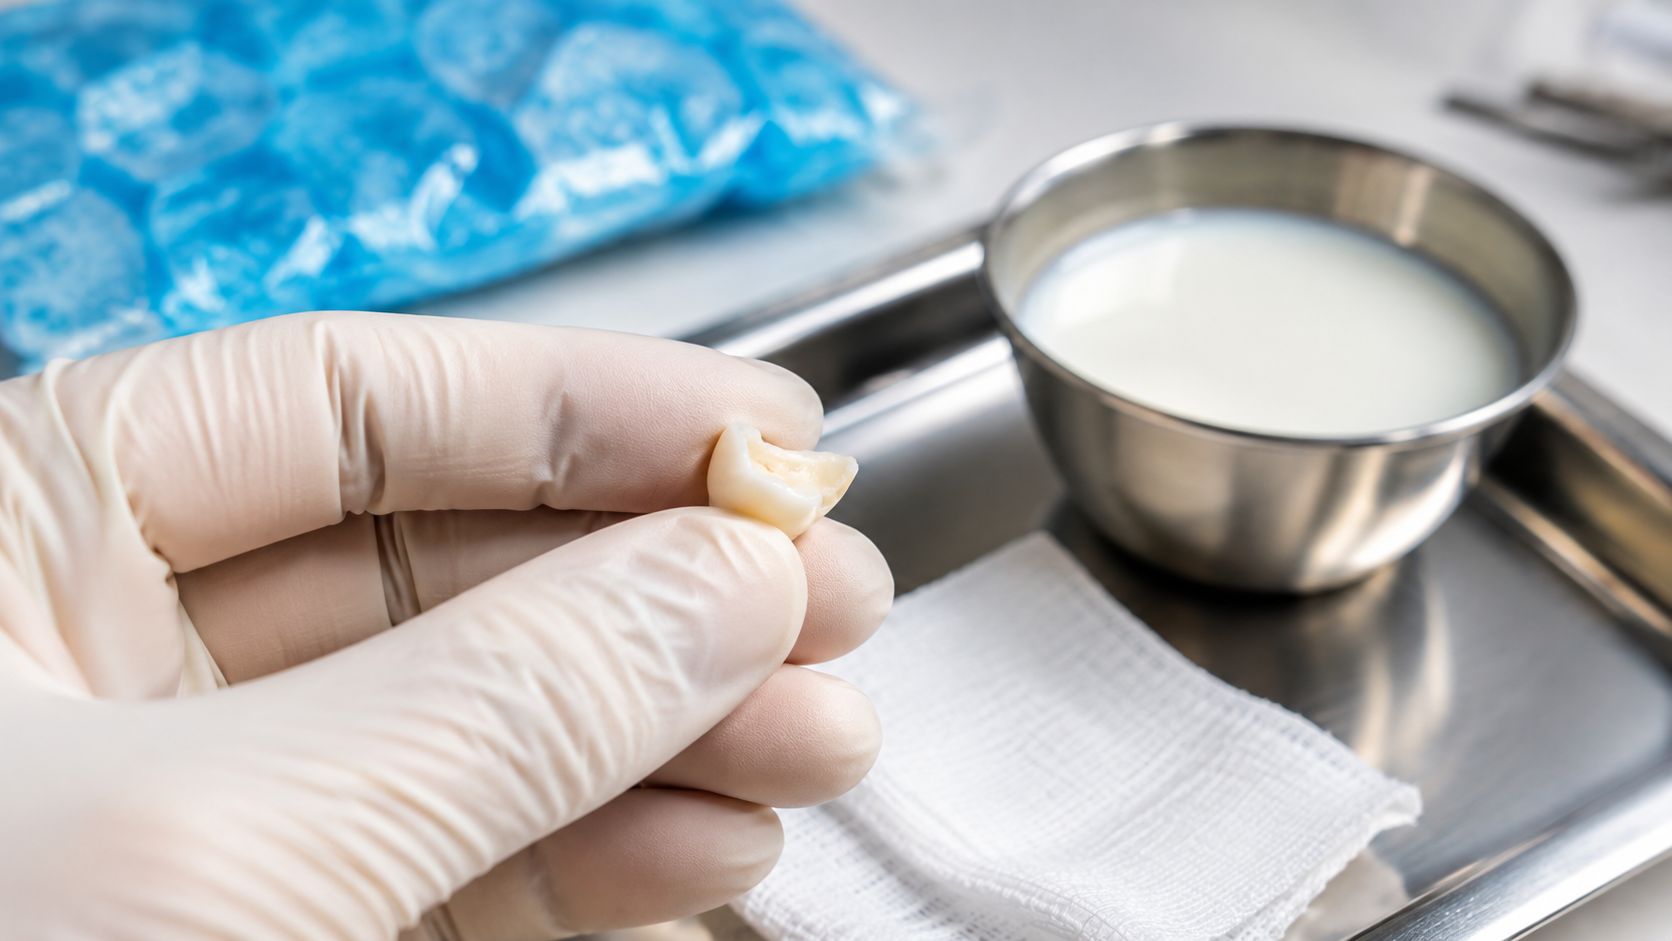
A Sydney patient often arrives after seeing an influencer video, holding a whitening pen or mail-order kit, and asking the same sensible question. Will this damage my enamel?
For healthy teeth, professionally supervised whitening is generally safe. The primary risk sits with unsupervised use, especially with products bought online, applied too often, or used on teeth that already have cracks, exposed roots, decay, worn enamel, or existing sensitivity. That distinction matters in a city as diverse as Sydney, where I see patients with very different dental histories, medical conditions, diets, and cosmetic goals.
Enamel is the hard outer shell of the tooth. It works like the clear protective glaze on ceramic. Whitening gels do not just scrape that layer away, but they do need to be used in the right concentration, for the right length of time, and on the right teeth. Used badly, even a product that sounds harmless on social media can push a manageable cosmetic treatment into a preventable problem.
At Lumina Dental, the first question is never just how white someone wants to go. It is whether whitening is appropriate in the first place, and how to do it without compromising tooth health. Temporary sensitivity can happen. Short-term surface changes can happen. Permanent enamel damage is far more closely linked to misuse, overuse, and poor case selection than to dentist-guided whitening itself.
If you want a practical overview before booking, our teeth whitening FAQ guide answers the questions patients ask most often.
The Quest for a Whiter Smile and the Enamel Question
Many individuals don’t want “Hollywood white.” They want their teeth to look fresher, cleaner, and more even, without trading long-term tooth health for a cosmetic improvement. That’s a reasonable goal, and it’s why the question “does teeth whitening damage enamel” comes up so often in the chair.
The answer depends far more on how whitening is done than on whitening itself. A dentist-supervised treatment starts with diagnosis. An unregulated strip or gel bought online starts with guesswork. Those are not the same thing, even if both products use peroxide.
Teeth whitening is safest when it’s treated like healthcare, not like a beauty hack. We assess whether the stains are the kind whitening can lift, whether the enamel is suitable, whether there are cracks, cavities, exposed root surfaces, or restorations that will affect the result, and whether sensitivity needs to be managed first.
Practical rule: Whitening should start with an examination, not a checkout cart.
That difference matters because people often confuse temporary sensitivity or short-term surface change with permanent destruction. They aren’t the same. Healthy enamel can tolerate carefully controlled whitening much better than many people realise.
For a broader overview of common patient concerns, our teeth whitening FAQs cover the practical questions people usually ask before booking.
Understanding How Whitening and Enamel Interact
Enamel is the outer shell of the tooth, but “shell” can make it sound like a smooth sheet of armour. A better analogy is a crystalline shield. It’s hard and protective, yet it has microscopic pathways within its structure. That’s why stains can settle in over time, especially from dark drinks, tobacco, and normal ageing.
Whitening works because those stain compounds aren’t just sitting loosely on top. Many are lodged within that outer structure. Brushing can remove surface debris, but it can’t reliably change deeper discolouration once it has settled in.
Enamel is strong, not solid like glass
People often imagine enamel as a pane of glass that whitening liquid somehow “burns through.” That isn’t how it works. Enamel is made of tightly packed mineral crystals. It’s durable, but it isn’t a featureless slab.
That matters because whitening agents don’t act like sandpaper. They don’t scrub stains off by grinding the surface away. Instead, they move through microscopic spaces and react chemically with the darkly coloured molecules responsible for staining.

What peroxide actually does
Hydrogen peroxide and carbamide peroxide are the common whitening agents in professional dentistry. They release oxygen that penetrates the enamel and breaks down stain molecules into smaller, less visible compounds. Think of it less like scraping graffiti off a wall and more like using a cleaner that dissolves the pigment without knocking the wall down.
Research on carbamide peroxide bleaching found no significant alterations to enamel topography on scanning electron microscopy, which supports the idea that professionally managed whitening targets stain chemistry rather than destroying enamel structure (study summary here).
That doesn’t mean nothing happens. Whitening can temporarily dehydrate the tooth and make it feel more reactive to cold air or drinks. Some patients describe a quick “zing.” That sensation is real, but it usually reflects a short-term response rather than lasting structural harm.
Why professional control makes such a difference
The same active ingredient can behave very differently depending on fit, exposure time, frequency, and the condition of the teeth underneath. A custom tray prescribed by a dentist is designed to keep the gel where it belongs. A generic strip or poorly fitting tray can push material onto the gums, miss some tooth surfaces, overload others, and tempt repeated use when the first result looks patchy.
That’s why supervision matters. It isn’t just about applying gel. It’s about matching the method to the person.
If sensitivity is one of your main worries, our article on teeth whitening and sensitivity explains why some teeth react more than others and what helps.
Whitening should oxidise stains, not become an uncontrolled experiment on your enamel.
The Scientific Evidence on Enamel and Whitening
The science on whitening is more nuanced than the internet usually makes it sound. If someone says whitening causes “no changes at all,” that’s too simplistic. If someone says whitening permanently ruins enamel, that’s also too simplistic. What the evidence shows is that temporary measurable changes can occur, and under professional protocols those changes usually recover.

Temporary microhardness changes are real
A 2023 study in the Australian Dental Journal found that professionally supervised in-office bleaching with 35% hydrogen peroxide caused an 18% temporary reduction in enamel microhardness, dentist-prescribed at-home gels caused a 12% decrease, and OTC products caused a 6% decrease. Natural salivary remineralisation restored microhardness in 85% of cases within 14 days, supporting the safety of professional cosmetic use under ADA guidelines (Australian Dental Journal study).
At first glance, that finding surprises people. They expect the strongest professional treatment to look safest in every short-term measurement. But short-term microhardness isn’t the whole story. In-office whitening is stronger, faster, and more controlled. The key point is that the change was temporary, and recovery occurred in most cases.
Why a bigger temporary change can still be safer
Context matters. A professionally supervised in-office session uses higher concentrations, but it also uses tighter control. The dentist limits the application time, protects the gums, checks the enamel beforehand, and gives aftercare designed to support recovery. OTC products often look “gentler” because the concentration is lower, but people can misuse them repeatedly, apply them too often, or continue long after sensitivity starts.
In other words, a lower concentration doesn’t automatically mean a lower real-world risk.
The safest whitening isn’t the weakest product. It’s the method with the best control.
Remineralisation is the body’s repair mechanism
Saliva plays a bigger role than is often realised. After whitening, minerals in saliva help restore the surface environment of the teeth. That’s why post-whitening advice matters. The tooth is more vulnerable to irritation if you combine whitening with acidic foods, aggressive brushing, or repeated unsupervised exposure.
A useful analogy is skin after a cosmetic peel. The skin hasn’t been destroyed, but it does need sensible care while it settles. Teeth behave differently, of course, but the principle is similar. Recovery depends on avoiding the habits that interfere with healing.
Damage versus reversible change
Patients often use the word “damage” to describe anything they can feel. Dentists have to be more precise. A brief increase in sensitivity is not the same as irreversible loss of enamel. A temporary shift in microhardness that normalises is not the same as long-term structural breakdown.
The clinical question is whether whitening, done properly, leaves teeth permanently weaker. Based on the evidence above, the answer for healthy enamel under professional supervision is generally no. The concern becomes much more serious when treatment is repeated too often, done on teeth that weren’t suitable in the first place, or performed with little regard for aftercare.
Comparing Whitening Methods Professional In-Office At-Home and OTC
If you want a practical answer to “does teeth whitening damage enamel,” compare methods the way a dentist does. Don’t just ask which one is strongest. Ask which one gives you the most control, the best fit, the safest timing, and the clearest plan if sensitivity appears.
A major problem in Sydney is that online whitening has been normalised as low-risk self-care. But a 2023 Australian Dental Association survey found that 42% of Sydneysiders had used unregulated whitening strips or gels bought online without dentist oversight, and 28% of this group reported enamel erosion symptoms (survey summary here). This is the main caution. Not whitening itself. Unsupervised use.
Teeth Whitening Methods Compared
| Feature | Professional In-Office (e.g. Zoom) | Dentist At-Home (Custom Trays) | Over-the-Counter (Strips/Gels) |
|---|---|---|---|
| Who assesses suitability | Dentist before treatment | Dentist before prescription | Usually no one |
| Fit and application control | High, with soft tissue protection | High, because trays are customised | Variable, often one-size-fits-most |
| Strength and speed | Faster visible result in clinic | Slower, more gradual | Variable and often inconsistent |
| Monitoring sensitivity | Immediate chairside monitoring | Guided by dentist instructions | Self-managed, often by trial and error |
| Risk if overused | Lower because frequency is controlled | Lower when instructions are followed | Higher because people often reapply |
| Best for | People wanting quick, supervised whitening | People wanting flexibility with professional oversight | People focused on convenience, despite less control |
What in-office whitening does well
In-office whitening is useful when you want speed and supervision in the same appointment. The concentration is higher, but so is the level of control. Soft tissues can be protected, the gel is applied evenly, and the session can be stopped or adjusted if the teeth respond strongly.
That control is why many dentists prefer in-office treatment for patients who are anxious about doing something wrong at home. There’s no guesswork about how much gel to use or whether a strip is sitting on the gumline.
Where custom tray whitening fits
Dentist-prescribed home whitening with custom trays sits in the middle. It gives you flexibility, but still keeps the process anchored to a diagnosis and an individual plan. The trays fit the teeth properly, which helps keep the gel on the enamel and off the gums.
For many adults, this is a sensible option because it balances comfort, convenience, and control. If you’re comparing treatment pathways, our guide to teeth whitening prices can help you weigh what you’re paying for beyond just the gel itself.
Why OTC products are the weakest option clinically
OTC products appeal because they’re easy to buy and easy to start. That’s also the problem. They bypass the part that protects you. No diagnosis, no customised fit, no check for cavities, no discussion of restorations, and no one to tell you whether the colour you dislike is even likely to respond to whitening.
People then chase a result with repeated applications. That’s where trouble starts. Patchy outcomes tempt extra use. Extra use raises irritation and sensitivity risk. And because no professional has assessed the enamel first, people may whiten teeth that were poor candidates from the start.
For readers comparing approaches beyond Australia, this discussion of teeth whitening in Chattanooga TN is a useful example of how dentists elsewhere also frame whitening around supervision, fit, and enamel protection rather than quick cosmetic promises.
If a whitening product’s main selling point is that you can start tonight without seeing a dentist, that convenience is also its biggest clinical weakness.
Identifying Your Risk Factors for Enamel Damage
Not every mouth is a good whitening candidate on every day of the year. That’s why a pre-whitening assessment matters. It isn’t a formality. It’s the step that separates a safe cosmetic treatment from a preventable problem.

Thin or worn enamel changes the equation
If enamel is already worn, whitening can feel harsher. A 2025 report from Dental Health Services Victoria indicated 35% higher whitening-induced sensitivity in patients with pre-existing enamel wear, with this highlighted as a concern for some Sydney demographics, including Mandarin and Cantonese speakers whose diets may be higher in acidic foods (report summary here).
That doesn’t mean people in those groups can’t whiten. It means they benefit from customized assessment and planning. Dietary acids, reflux, clenching, and past erosion all change how the teeth may react.
Common reasons to pause or modify whitening
A dentist will usually be cautious if any of these are present:
- Visible cracks or chipped enamel can make sensitivity more likely and can lead to uneven results.
- Untreated decay needs treatment first. Whitening over a cavity is asking an already irritated tooth to cope with more.
- Exposed root surfaces don’t behave like enamel and can react sharply.
- Crowns, veneers, and fillings won’t whiten the same way natural enamel does, so the colour match can become worse rather than better.
- Existing sensitivity doesn’t always rule whitening out, but it often changes the approach.
Not all staining is the same
Some people assume every dark tooth will lighten if the gel is strong enough. That isn’t true. External stain from coffee or smoking behaves differently from internal discolouration due to trauma, ageing, medicines, or old restorations. If the cause is different, the right treatment may be different too.
That’s one reason online kits disappoint people. They sell one answer for many different problems.
A whitening assessment isn’t about selling treatment. It’s about ruling out the reasons treatment might be the wrong first move.
The local factor matters
Sydney is diverse, and oral health patterns vary with diet, habits, and dental history. In practice, that means one patient may have sound enamel and surface staining, while another has acid wear, old composite fillings, and chronic sensitivity. Both may ask the same question. They don’t have the same risk profile.
A real difference can be achieved through a calm, multilingual consultation. Patients explain their habits more clearly when they feel understood, and that helps us make better clinical decisions.
How to Whiten Your Teeth Safely in Sydney
Safe whitening starts before any gel touches the teeth. The first step is a clinical check to see whether whitening is appropriate, which method suits you, and what needs to be managed first. That includes looking for cracks, cavities, leaking fillings, wear, gum recession, and colour mismatches with existing dental work.

What a safe whitening plan usually includes
In Australia, professional in-office bleaching protocols using 25% to 35% hydrogen peroxide for 1 to 2 sessions preserve enamel microhardness, and using desensitising agents with 5% potassium nitrate can reduce sensitivity by up to 40%. The same clinical guidance also notes that acidic foods after treatment can soften the enamel pellicle, which is why aftercare matters so much (clinical summary here).
A sensible whitening plan usually includes:
- A suitability check first so whitening isn’t done over untreated disease or on teeth likely to react badly.
- The right method for your enamel rather than the strongest option by default.
- Sensitivity management if you’ve had zingers before or already know your teeth run sensitive.
- Clear aftercare instructions so the teeth settle properly after treatment.
The first two days matter
After whitening, teeth are more likely to pick up stain and react to irritants for a short period. That’s why dentists often advise a “white diet” for the next couple of days. The idea is simple: if it would stain a white shirt, don’t rush to put it on freshly whitened teeth.
That usually means being cautious with coffee, tea, red wine, richly coloured sauces, and acidic foods for a short window. Good hydration and gentle oral hygiene help more than aggressive brushing.
For readers who like hearing another dentist’s patient-safety approach, this article on trusted cosmetic care at Dr. Salami's office is a useful example of the same principle. Whitening works best when the process is individualised rather than improvised.
Here’s a short visual overview of how professional whitening is typically performed in clinic:
Where to start if you’re unsure
If you’re considering whitening in the CBD or inner Sydney, start with a consultation rather than a product search. At Lumina Dental’s teeth whitening page, you can see the type of professionally supervised treatment pathway patients usually discuss before deciding whether in-chair whitening, custom trays, or no whitening yet is the right call.
If you’re nervous, say so early. Sensitive teeth, previous bad experiences, and uncertainty about colour outcomes are all manageable when they’re part of the plan from the start.
Achieving a Confident Smile Without Compromise
A patient comes in after trying a whitening hack seen on TikTok in the morning and asks me, by the afternoon, whether the enamel is gone for good. I hear versions of that question often in Sydney, especially after charcoal pastes, lemon-based home remedies, bargain kits bought online, or whitening strips used far more often than the instructions allow. The risk is higher for patients who already have sensitivity, enamel wear, reflux, dry mouth, gum recession, or older fillings and crowns.
Enamel does not grow back, so whitening needs the same care as any other treatment that affects tooth structure. The chemistry of proper whitening is more controlled than many people assume. Peroxide works like a stain-lifting rinse moving through tiny channels in the tooth, not like sandpaper scraping enamel away. Trouble usually starts with the wrong product, the wrong frequency, or whitening teeth that should have been examined first.
That is the answer to the question, “does teeth whitening damage enamel?” Safety depends on fit. A treatment that is reasonable for one patient can be a poor choice for another.
Sydney’s DIY trend culture often ignores that difference. A social post cannot tell whether white patches are early enamel weakness, whether dark areas are stains or decay, or whether a patchy result is coming from old bonding on the front teeth. A clinical assessment can. That matters in a city as diverse as ours, where patients present with different diets, medical histories, cultural habits, and previous dental work that all affect whitening safety.
Whitening is also only one option in cosmetic care. If you are weighing it against other treatments, our guide on whether veneers require shaving teeth explains how the trade-offs differ when the goal is colour, shape, or both.
For patients in Ultimo, Pyrmont, Glebe, and the Sydney CBD, the sensible next step is an assessment with a dentist who will tell you candidly whether to proceed, modify the plan, or wait. At Lumina Dental, that conversation is straightforward. Some patients can whiten safely now. Some need a scale and clean, fluoride support, or sensitivity management first. Some should avoid whitening for the moment because protecting the enamel matters more than chasing a brighter shade.
That is still a good result.